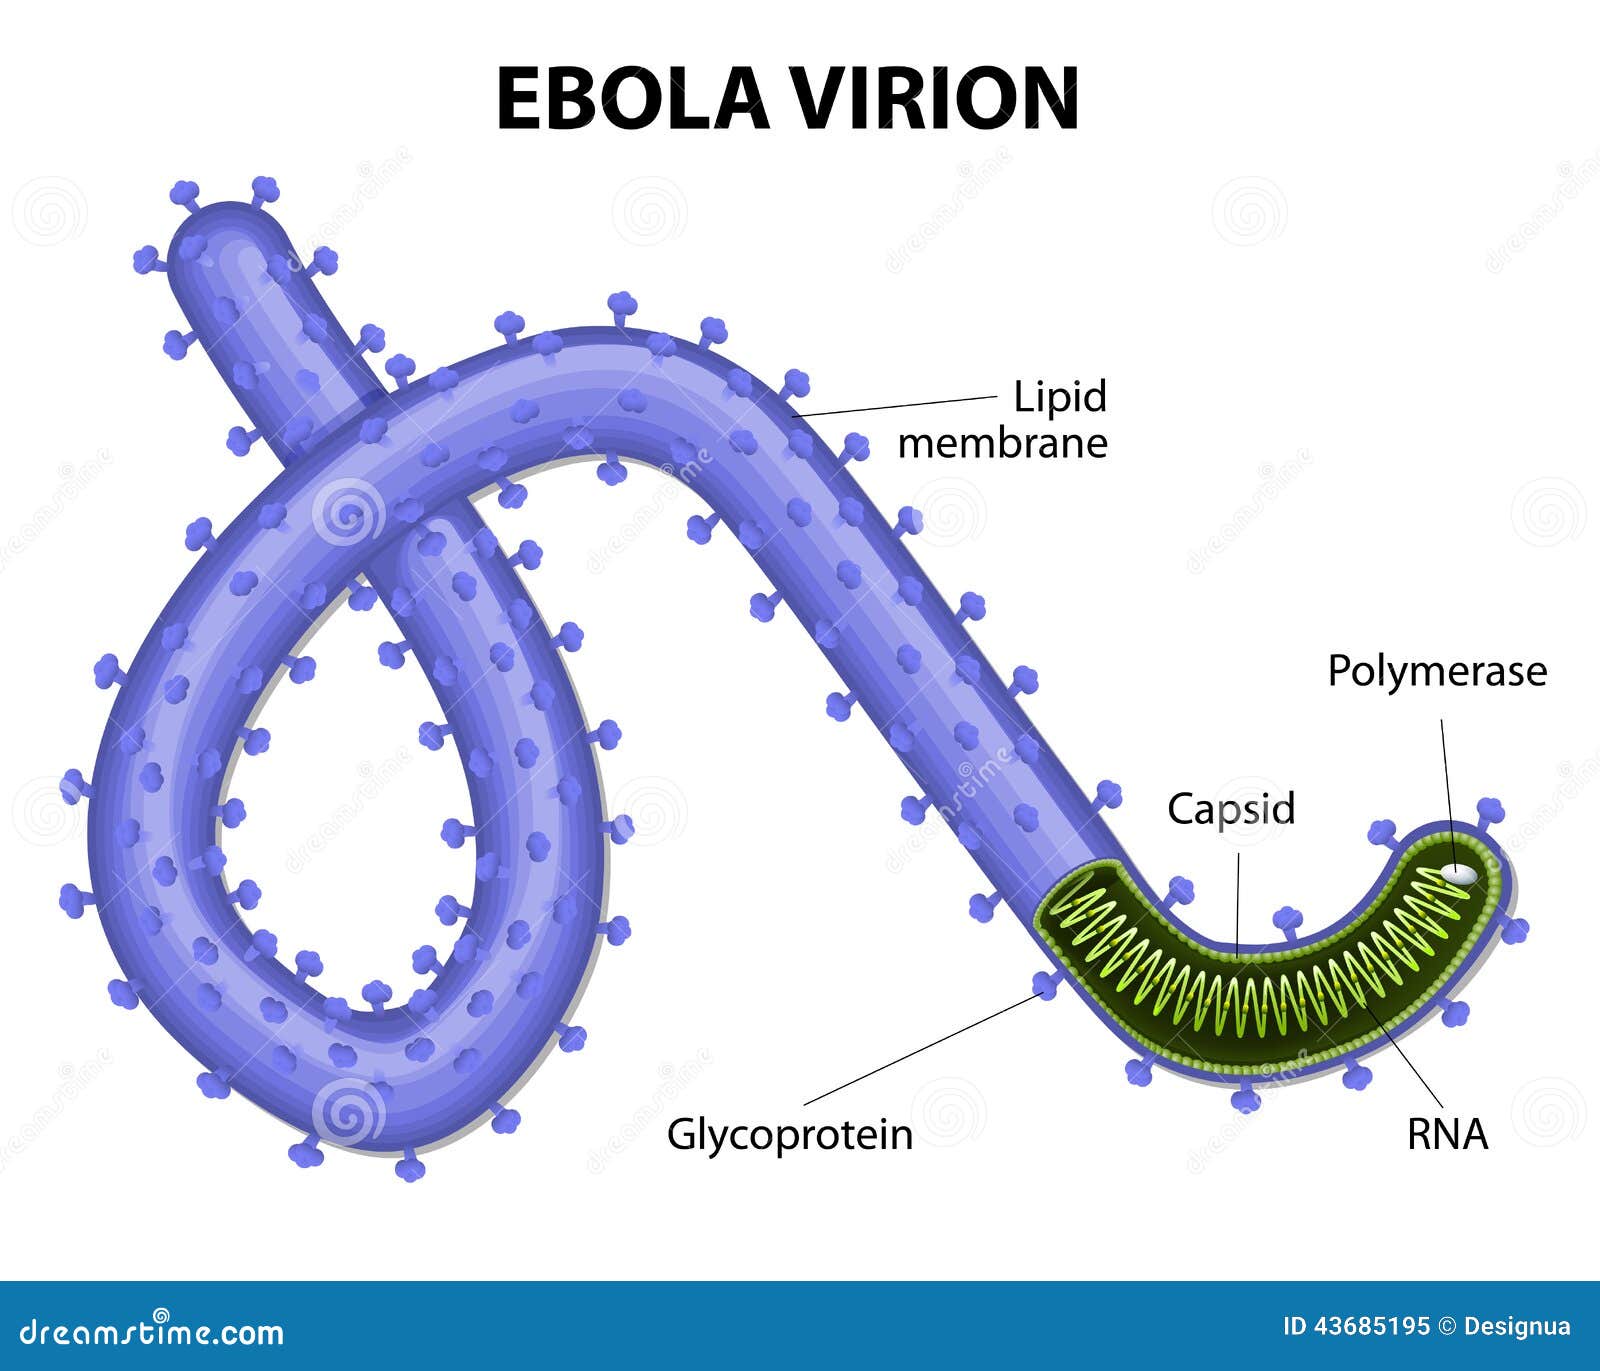
Four thousand lives lost. A staggering mortality rate nearing fifty percent. The Democratic Republic of Congo is once again caught in the agonizing grip of a relentless viral storm, and the world is not paying close enough attention.
When you hear about outbreaks happening thousands of miles away, it's easy to tune it out. You scroll past the headlines. You assume local health agencies have everything under control. But the reality on the ground in Central Africa tells a much harsher story. The numbers are climbing, and medical teams are running out of time.
The Brutal Reality of the Bundibugyo Strain
Let's address what makes this current wave so terrifying. We aren't dealing with a familiar variant that scientists have spent decades cracking. The culprit driving these numbers is the Bundibugyo strain of the Ebola virus.
Why does that matter? Because there is no approved vaccine or specific targeted treatment for this particular strain.
Think about that for a second. In an era where biotechnology moves at lightning speed, public health workers are fighting a high-mortality pathogen with one hand tied behind their backs. Supportive care—rehydration, managing blood pressure, treating secondary infections—is basically all they have. When a virus kills roughly forty-eight out of every hundred people it infects, supportive care feels like bringing a knife to a gunfight.
Why DR Congo Becomes Ground Zero
If you study modern epidemiological history, the Democratic Republic of Congo features far too often as the epicenter of viral hemorrhagic fevers. It isn't bad luck. It's a combination of geography, infrastructure challenges, and deeply entrenched socioeconomic hurdles.
The Congo Basin is vast, dense, and difficult to navigate. Remote villages where outbreaks frequently start often lack basic paved roads, reliable electricity, or functional cold chains required to store sensitive medical supplies.
When symptoms start—sudden fever, severe fatigue, muscle pain, headaches, followed by vomiting and bleeding—infected individuals often rely on traditional healers or travel long distances to urban centers, inadvertently spreading the virus along transit routes. Local health infrastructure buckles under the pressure almost instantly.
The Trust Deficit and Community Resistance
Medical interventions don't happen in a vacuum. You can have all the protective gear and experimental drugs in the world, but if the local population distrusts outside health workers, containment fails.
Years of civil conflict, political instability, and historical exploitation by foreign powers have left many communities deeply skeptical of government directives and international aid organizations. Rumors spread faster than the virus itself. When panic sets in, families hide sick relatives at home rather than sending them to isolation treatment centers, unknowingly exposing every single person in their household.
Public health strategy has to evolve past just dropping medical supplies from helicopters. Building genuine trust, engaging local community leaders, and respecting burial traditions without compromising safety are the real battlegrounds of outbreak control.
What Needs to Happen Right Now
Sitting thousands of miles away, it's easy to view this as someone else's distant tragedy. Viruses do not respect borders. A localized epidemic left uncontained can quickly transform into a regional crisis with global implications.
International funding needs to shift from reactive emergency responses to proactive surveillance and research investments. We need accelerated clinical trials for therapeutics targeting the Bundibugyo strain. We need robust local laboratory networks that can catch a mutation or a new cluster within forty-eight hours instead of weeks.
Ignore the noise and look at the data. The outbreak in DR Congo is a brutal reminder that humanity's grip on deadly pathogens is fragile. If the global community doesn't step up with sustained, long-term backing for local health systems, we will continue reacting to tragedies instead of preventing them.